<img height="1" width="1" style="display:none;" alt="" src="https://px.ads.linkedin.com/collect/?pid=5387194&amp;fmt=gif">

Delivery Partner

For the problems technology can't quite reach

What stalls outpatient transformation rarely shows up in the data. It shows up in clinics, in booking teams, in the habits nobody ever wrote down. Finding it is where we start. Fixing it is what we get paid on.

THE GAP WE FILL

Everything that decides the outcome happens in between.

Pathway change, process work, and the people living with both.

Pathway change, process work, and the people living with both.

That middle job is one few take on - but we do.

Where benefits are realised or lost

Strategic consultancy

The messy operational reality

Technology vendor

Identify opportunities and build plans
Clinical pathway transformation
Operational process improvement
Human change management
Build features and functions
Only DrDoctor does all three.

PAY FOR OUTCOMES, NOT PROJECTS

Outcomes, not a deck 

You commission a set of results, not a project that finishes with a presentation. These are the kinds of outcome we are held to, with part of our fee riding on them.

Return on investment

Money back against what you spend with us, counted from your own finance data rather than sector benchmarks.

cash and non-cash savings

Capacity released

Appointments that already exist inside the clinics you run, freed up without new estate or new staff.
capacity protected

Admin time saved

Hours taken off admin and handed back to teams who need them, rather than taken out as headcount.

admin savings

HOW IT WORKS

Diagnose. Design. Deliver

Before we touch a single system, we get clear on where the real problems are. We diagnose what needs fixing, design the solution around your local context, and deliver the change.

01

Where others start with a solution

We start by sitting in your clinics

Weeks on-site, in clinics, in booking teams. Before we touch anything, we need to understand what's actually going wrong. Not just what's said in the board papers.

FIXED-PRICE DIAGNOSTIC
02

Where others give you an opinion

We show you where you sit nationally

Performance against peer trusts on utilisation, follow-up booking and DNA rates, plus a readiness-for-change assessment. Evidence, not opinion.

FIXED-PRICE DIAGNOSTIC
03

Most leave you a plan

We stay in the room until it's tuned to your context

Every implementation plan co-built with the people who have to live with it. Nothing works if it's imposed.

RISK-SHARED PARTNERSHIP MODEL
04

Many disappear at go-live

We don't leave until it sticks

The same regional transformation lead carries through delivery, resolving blockers and keeping momentum to measured impact.

RISK-SHARED PARTNERSHIP MODEL
READINESS ASSESSMENT

Assessing readiness for change

We look across six key dimensions of the organisation to assess change readiness.

People & Case for Change
  • Passion for patient care is high
  • Vision for change needs to be unified and owned
Leadership & Ownership
  • Sponsorship is visible
  • Follow-through at pace is the gap
People, Capability & Capacity
  • Change fatigue is real
  • Roles for improvement need clarity
Readiness radar chart
  • People & Case for Change: 78 out of 100
  • Leadership & Ownership: 62 out of 100
  • People, Capability & Capacity: 45 out of 100
  • Ways of Working & Process: 50 out of 100
  • Systems, Tools & Use of Data: 38 out of 100
  • Culture, Behaviour & Belief: 72 out of 100
Ways of Working & Process
  • Processes exist on paper
  • Inconsistently applied in practice
Systems, Tools & Use of Data
  • Data confidence is variable
  • Decisions aren't consistently data-led
Culture, Behaviour & Belief
  • Appetite for change exists
  • The structure to sustain it is needed

WHAT YOU GET

A shared blueprint,
not a generic report

Clinic studies, case reviews, booking practice, opportunities sized and sequenced, and a costed implementation plan. Every page built from your own data, and co-designed with the people who have to live with it.
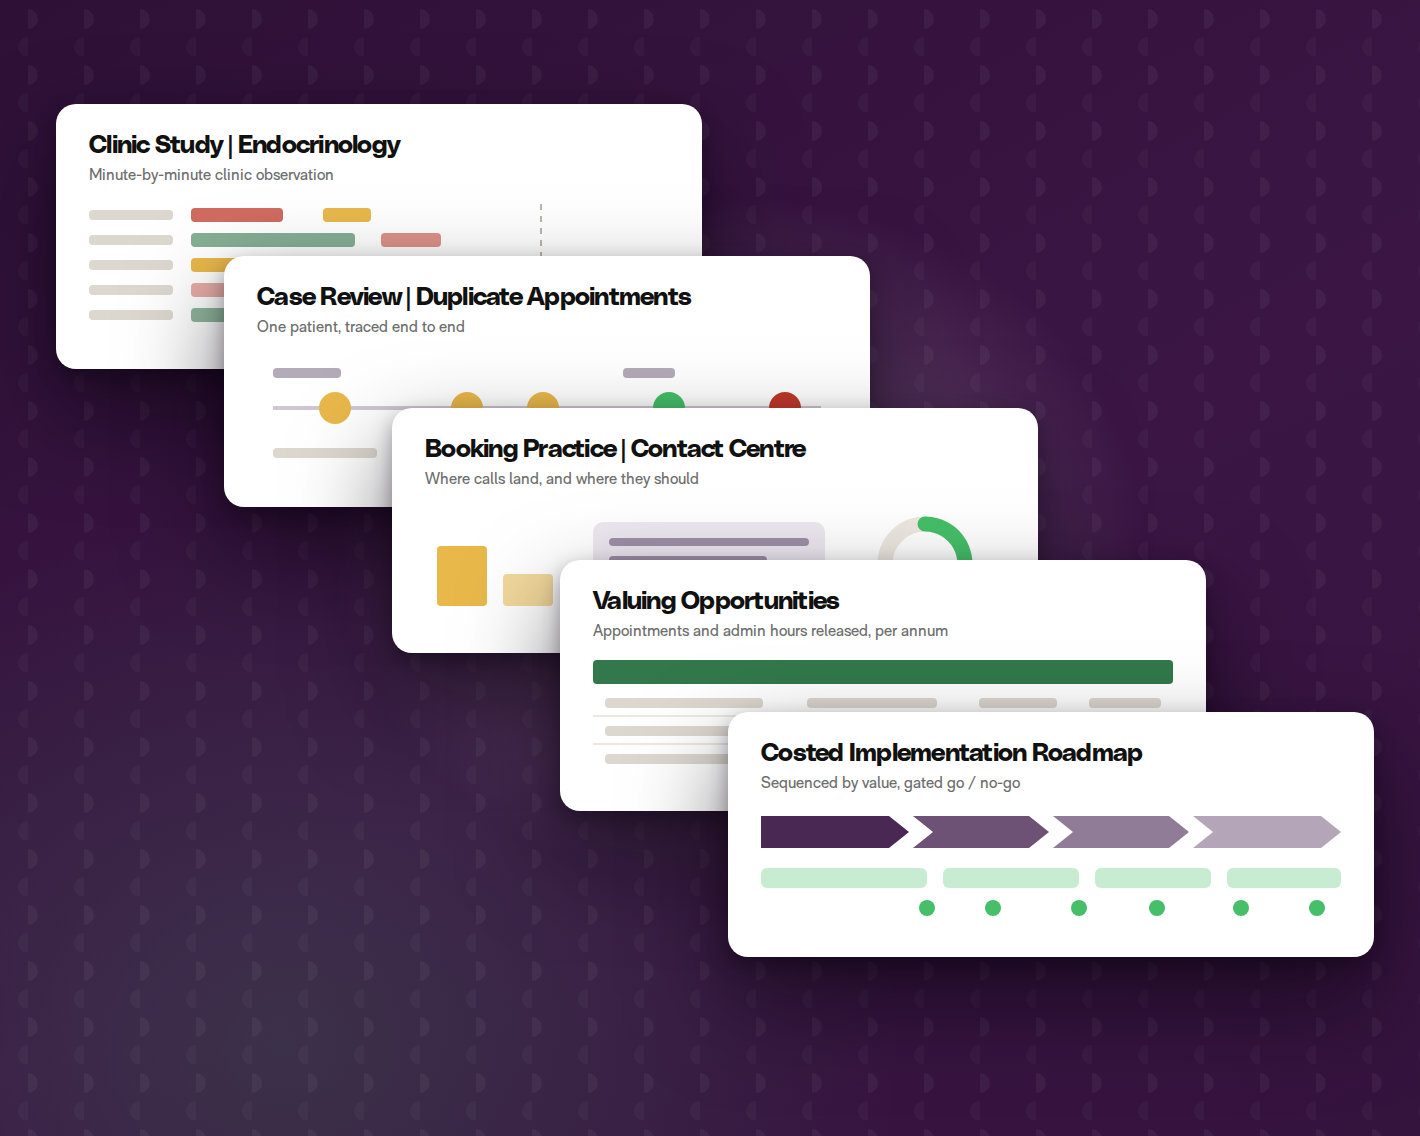
what-you-get-C-spotlight-1420x1136

Measuring the impacts

How will you know it's worked?

Example measures. The real set is co-designed with you during the diagnostic.

Where a large acute trust typically starts, benchmarked against our data

Clinic utilisation

40-45%

Where it should sit: 50-75%

Bookings made per appointment actually attended

1.6

Where it should sit: 1.2-1.3

Patients seen per four-hour clinic block

5

Where it should sit: 10-15

Steps to reach a clinical outcome

7-9

Where it should sit: 5-6

By service

Monthly

  • Capacity released
  • Clinic productivity
  • Slot fill rate, including DNAs and vacant slots
  • Admin hours released

By pathway

Per cohort

  • Demand reduction through A&G and triage
  • Avoided duplication
  • Follow-ups avoided
  • Patient experience

By trust

Quarterly, to the board

  • Total benefit realised
  • Cash-releasing saving
  • Staff experience
  • Impact on RTT and performance

PUTTING BOOTS ON THE GROUND

Because some things don't always show up in the brief

Here's the sort of things we find when we get up close. None of it comes from a survey or a data pull.
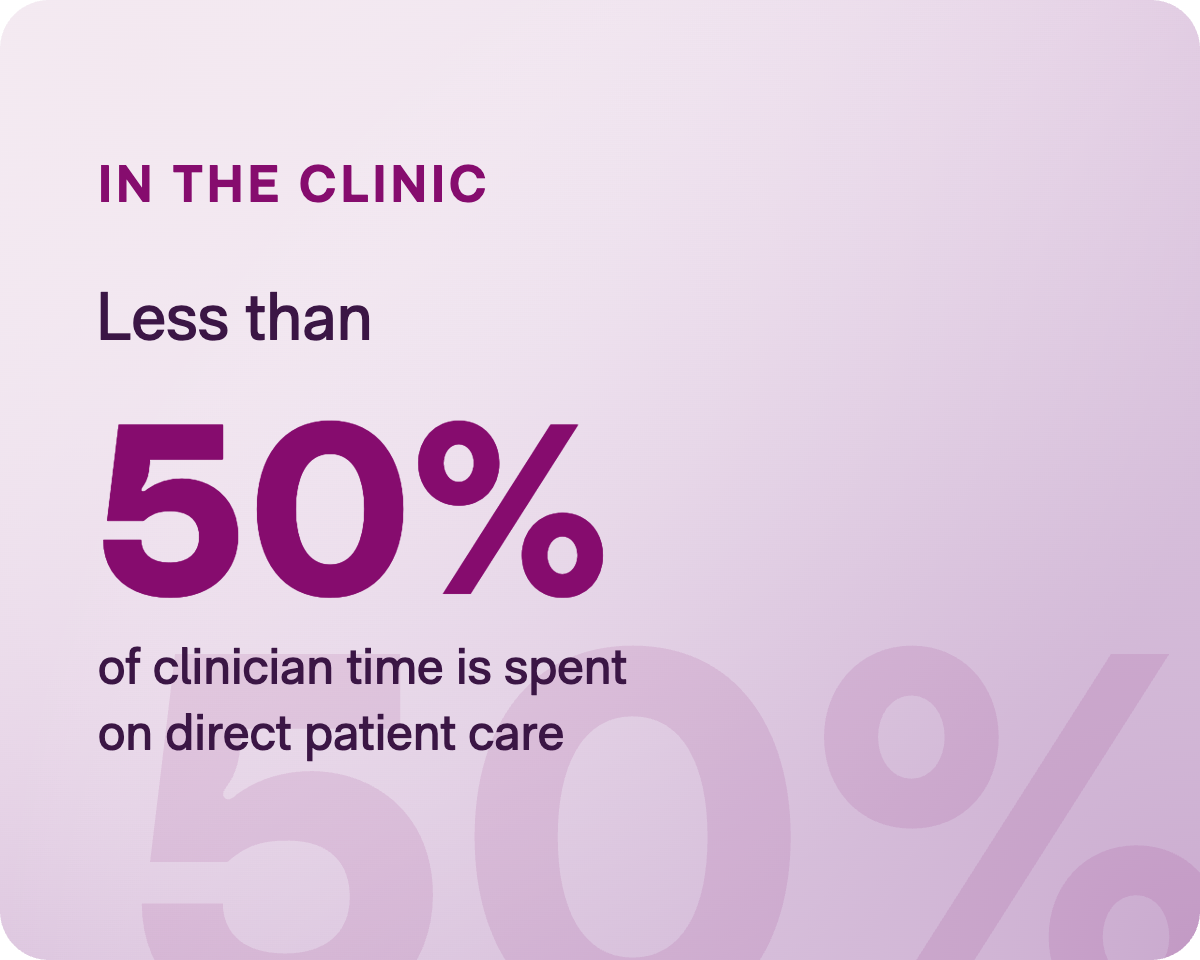
In the clinic - less than 50 percent

The EPR said delays. We found something else

Less than half of clinician time in an outpatient clinic went on direct patient care. The rest was dictation, IT workarounds, chasing referrals, waiting. In the record it all looks the same. You only see it by sitting in the room.

DrDoctor have worked on the ground with our clinical and operational teams to help us really understand the constraints in our current outpatient model, and more importantly, to co-design a future model that will support improved operational and financial performance.

Lesley Terry UHCW

Lesley Terry

Strategy and Transformation | University Hospital Coventry and Warwickshire

RISK-SHARE PRICING MODEL

Part of our fee only lands when the outcomes do

Agreed with you at baseline. Measured on your numbers, not ours.

THE INITIAL DIAGNOSTICS

A fixed cost, and a fixed end date

Five to six weeks, from mobilisation to a board-ready blueprint

Fixed cost and fixed scope, not an open-ended consultancy retainer

Commissioned without a full tender in most trusts we work with

The roadmap is yours, co-designed with your operational and clinical leaders

THE DELIVERY MODEL

A bigger fee, and a share of it at risk

You commission an outcome, not a set of features and functions

Part of our delivery fee is held back until the agreed outcomes are measured

A programme rather than a project, sequenced by value and delivered in phases

One blended team, led by the same person who ran your diagnostic

Think we might be a good fit?

Enquire about our delivery partner programme today.
